

HCP engagement is how a pharma company builds its relationship with healthcare professionals (HCPs): the doctors, pharmacists and nurses who prescribe, dispense or advise on its medicines. In Kenya, Nigeria and much of Africa, most of that relationship still runs through the medical rep’s visit to the clinic and the chemist counter.
A rep in Nairobi details a doctor on Monday. By Friday, nobody knows if the chemist across the road stocks the brand. In Lagos, the script may be filled at a patent medicine shop supplied by a wholesaler you have never met. Pharma SFA closes that gap: each call starts from what the last call, the nearby chemist and the last CME showed.
What HCP engagement covers in the field
For a medical rep, HCP engagement is more than the visit. It covers the call, a remote detailing session when a clinic is too full, CMEs and seminars, the samples a doctor signs for, and the follow-up at the chemist next door.
Pharma SFA (sales force automation) holds all of it. It is the app on each rep’s phone plus the system managers use to approve and review the work. To see the product itself, go to BeatRoute’s pharma SFA software page.
Where the doctor’s script goes after the call
In Kenya and Nigeria, many prescriptions are filled at an independent counter, not a hospital pharmacy with its own data. That may be a chemist down the street, a duka la dawa in a Kenyan town, or a patent and proprietary medicine vendor (PPMV) in Nigeria. Many restock from wholesalers and open drug markets such as Idumota in Lagos, not only from your distributor.
So the link that matters most is between the doctor and the counters near their clinic. BeatRoute sets it up when the doctor is added: each doctor is tied to the chemists around them. Later a rep runs a retail chemist prescription audit (RCPA) at one of those counters to note which brands it dispenses. The audit lands on that doctor’s record by itself.

Put side by side, the two records show what the rep detailed and what the counter really sells. A chemist fills scripts from many doctors, so this never proves one prescriber’s habits. It is still the best field evidence you will get that a detailing message is reaching patients.
CMEs and seminars work the same way. BeatRoute runs them from budget request to approval to attendance, tagged to each doctor who came. A rep sees that a doctor sat through two CMEs before the visit. The events team can read dispensing at nearby chemists afterwards as a direction, not a result per doctor.
Building the call plan: which doctors, and how often
The plan rests on a clean doctor list. For each doctor it holds the specialty, the clinic location, the chemists close by and a class per brand. Monthly tour plans then decide visit frequency by class. The area manager signs them off before the month opens, so no top prescriber is left out.
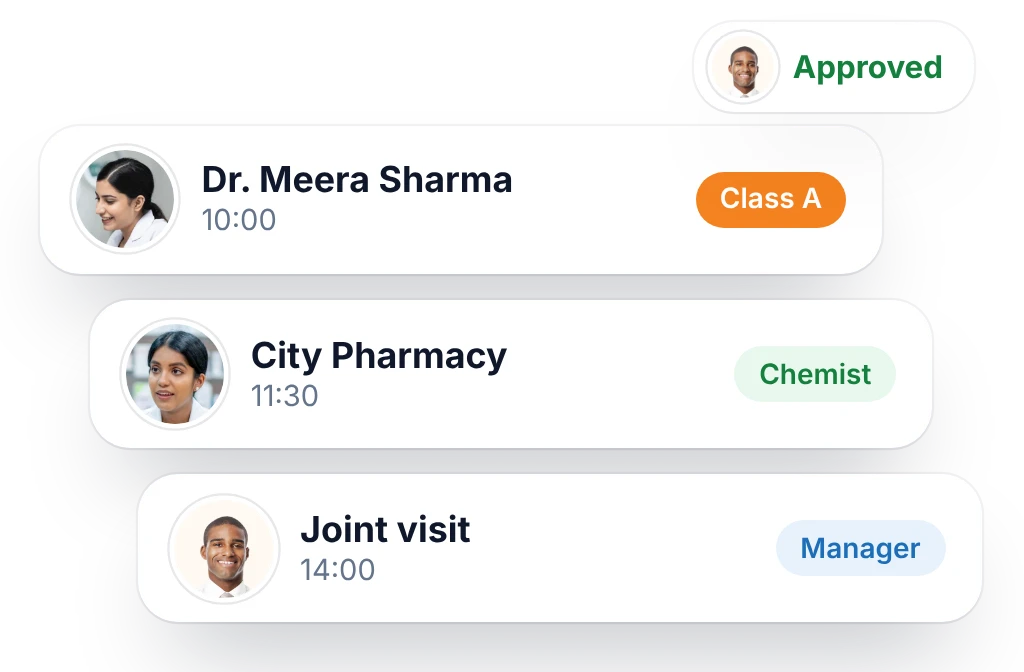
A class set from memory differs from rep to rep, walks out the door when a rep resigns, and never flags a doctor whose prescribing has quietly shifted.
In BeatRoute the class comes from evidence reps already collect: RCPA results, sample history and what each visit produced. On top of that record, the Customer Insights AI Agent from BeatRoute’s Goal-Driven AI writes a short agenda for every call, so the rep walks in knowing what to raise.
In the consulting room: call forms, e-detailing and samples
One form for every doctor gives call reports that prove a visit happened and little more. In BeatRoute, your team sets every field on the call form without IT work, and a field shows only when it applies. A rep detailing a new antibiotic to a paediatrician sees the paediatric questions, nothing meant for a GP.
Each e-detailing session saves what was shown, for how long and how the doctor responded. Brand teams see which content holds a doctor’s attention and drop what doctors skip next cycle.
Every sample pack and gift is counted as it moves from the depot to the rep’s bag to the doctor, who signs for it. The rep’s balance stays current, and auditors can follow each pack.
Measuring HCP engagement before the cycle closes
Three signs show the engagement is working: top doctors seen as often as their class asks, e-detailing sessions doctors stay through, and nearby counters dispensing more of the brand.
Most managers find the doctors nobody saw at month-end, when the cycle is already gone. BeatRoute compares the plan with actual calls every day. If a zone slips under its visit norm, an alert reaches the manager in time to move reps around.
A manager can also type a question to BeatRoute Copilot, for example: which Class A doctors in Mombasa have had no call for two weeks?
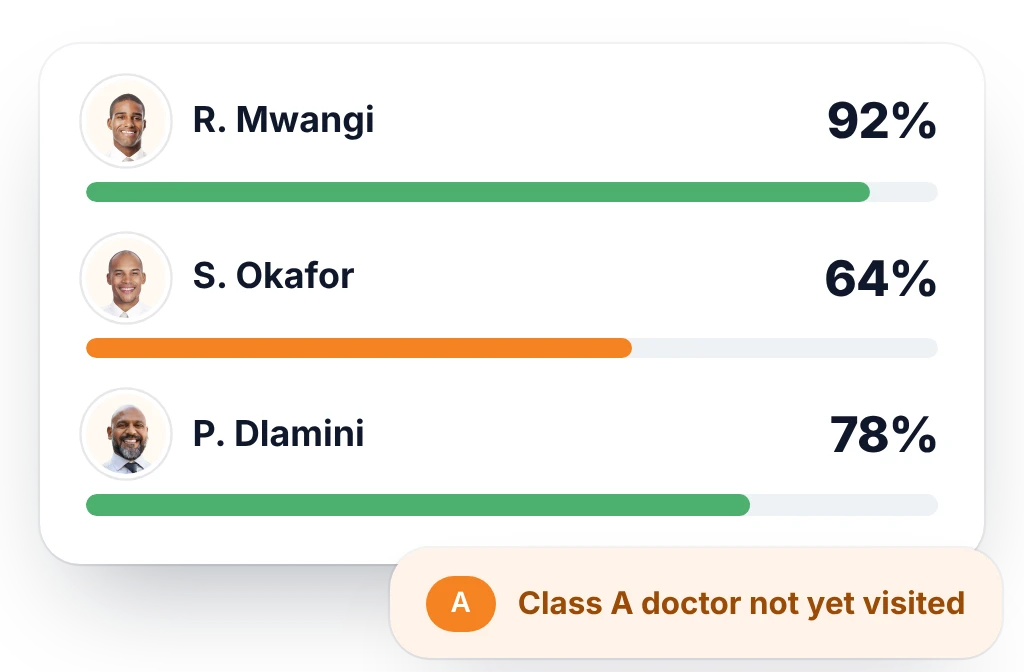
When the manager rides along, the joint call goes into the app with a rating, so coaching comes from what the manager saw. Once a report is submitted it cannot be quietly changed: each edit carries a name and a time. That record protects a good rep at incentive time.
Teams moving from call counts to goals can read our guide from sales force effectiveness to AI-driven SFA.
How the setup changes with your portfolio
| Portfolio | What the field work looks like | What to test first |
|---|---|---|
| Specialty prescription brands | Few specialists in teaching and private hospitals, longer calls, more CMEs | Call forms per specialty, doctor profiles, CME attendance |
| Branded generics and primary care | Many GPs on a tight visit frequency, scripts filled at nearby chemists and PPMVs | Tour plans, visit norms, doctor-to-chemist links |
| OTC and consumer health | Chemist and PPMV coverage, orders through stockists and wholesalers | Orders booked at the counter and stockist secondary sales (see SFA for consumer goods) |
Field or digital engagement: SFA, CRM or DMS
SFA runs the field day: the plan, the call, the audit. A pharma CRM looks after the doctor relationship over years, often through email and webinars run by marketing or medical affairs.
Decide by where your doctors actually meet your brand. If reps in clinics and chemists carry most of it, pick an SFA with a complete doctor record; if email carries most of it, a CRM-first product may suit you better. The general difference is in our guide to SFA vs CRM.
A DMS (distributor management system) runs the stock, orders and claims of the stockists behind the counters. OTC teams often link it to the SFA, so a chemist order reaches the stockist without being typed twice. See BeatRoute’s distributor management system.
Testing a pharma SFA in your own territories
Ask for these six things on your own data, not on a demo script:
- Put the phone in flight mode, run a rep’s full day of calls, then reconnect and sync.
- Add a question to the paediatric call form on the spot, without calling a developer.
- Give a rep a box of samples, hand some to doctors, and check that the month-end balance comes out right.
- Audit a chemist and show which doctor visits the audit links to.
- Open one doctor’s page and show the calls, chemist audits and CMEs together.
- Halfway through a cycle, show an area manager where coverage stands against plan.
Pilot one strong territory and one weak one, such as a city team and an upcountry team. Write down four numbers first: top doctors covered, visit frequency achieved, sample balances that reconcile, and hours managers lose to reports. Run a whole cycle, so the mid-cycle alerts are acted on before you compare.
In Nigeria, AAVA Brands runs its field team and distributors on the BeatRoute platform and grew field force productivity by 18–20% and store-level sellouts by 25–30%. AAVA sells consumer goods to shops, not medicines to chemists, so take it as a result from Nigerian field teams rather than a pharma one. Read the AAVA Brands case study.
BeatRoute suits pharmaceutical companies and consumer health brands with large teams of medical reps who want detailing and call reporting in the same app. BeatRoute is subscription software, priced per user and module on annual contracts, with no free trial. Book a demo to see call forms and doctor profiles set up for your own specialties, brands and territories.
Frequently Asked Questions
How is pharma SFA different from MR reporting software?
MR reporting software handles the daily call report (DCR) and the manager’s check of it. Pharma SFA holds that report too, inside a bigger system with the tour plan, doctor record, samples and chemist audits. If daily reporting is all you need for now, see our guide to MR reporting software.
Can reps detail doctors remotely?
Yes. The rep shows the approved content over a video call, and the session is saved on that doctor’s record like a face-to-face call. More in our page on e-detailing software.
Does the app work when the network drops?
It does. Reps record calls, samples and chemist audits with no signal, and the app syncs when the phone reconnects. Run the flight-mode test on the handsets your reps really carry.
How long does a pharma SFA rollout take?
Most BeatRoute teams go live in 21 days. Large pharma companies take longer, more so when prescription and OTC teams each need their own setup.
