

Most Philippine medrep teams already run on some kind of system. The MD list sits in Excel, the day’s call report reaches the district manager on Viber at night, and the drugstore RCPA lives in a separate sheet. None of them tells a PMR waiting outside a clinic in Cebu what this doctor needs to hear today.
A good pharma SFA puts them on one doctor record, so each call starts from the last call, the drugstore beside the clinic and the last CME the doctor attended. This guide is for the district and national sales managers who choose and run that system.
What pharma SFA covers for a medrep team
Pharma SFA (sales force automation) is the phone app and manager system a pharma field force works on every day. Professional medical reps (PMRs), OTC reps and hospital key account managers use it to plan and log their calls on doctors, drugstores and stockists. District managers and head office use it to approve call plans, check calls and follow sales by territory.
The person at the center is the healthcare professional (HCP). That is mostly the doctor, and often the pharmacist at the drugstore too. For the product itself, see BeatRoute’s pharma SFA software page.
SFA or pharma CRM: which one do you need first?
Many vendors sell both under one label, so choose by where your doctor contact happens. If most of it is a PMR in the clinic, start with an SFA that keeps the whole doctor record. If most of it is email and webinars run by marketing or medical affairs, a CRM-first tool may suit you better. Our SFA vs CRM guide covers the general split.
Building the MD list and the call plan
Everything starts with the MD list, the doctor master. Each doctor carries a specialty, a clinic or hospital, the drugstores near them and a prescriber class for every brand. The monthly call plan sets how often each class gets a visit. The district manager approves it before the cycle opens, so no high-value doctor drops off the plan.
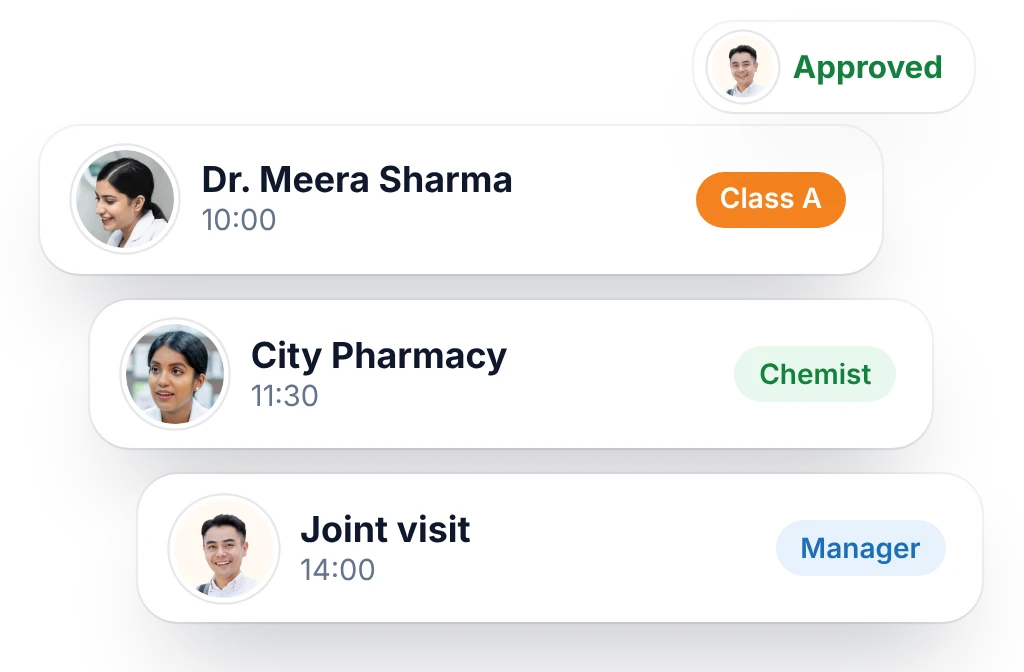
When reps key in doctor classes themselves, two PMRs can rate the same doctor differently, and nothing flags a shift in prescribing.
BeatRoute builds the class from what the field records instead: RCPA audits, samples given and the outcome of each visit. The Customer Insights AI Agent, part of BeatRoute’s Goal-Driven AI, turns that history into an agenda for the visit. The rep walks in knowing what to bring up with that doctor.
Inside the clinic: call reports, e-detailing and samples
One report form for every specialty gives you DCRs that prove a visit happened and say little more. In BeatRoute, your team sets each field of the call form with no IT ticket, and a field shows only when it applies. A PMR presenting a new molecule to a pulmonologist gets the questions for that call and nothing else.
Every e-detailing session logs what was shown, how long the doctor stayed with it and how they responded. It sits next to the doctor’s class, past calls and drugstore audits. Brand teams use this HCP data for field force effectiveness. They compare what each doctor saw with what nearby drugstores later dispensed, then change next cycle’s content.
Samples and giveaways move from stock to rep to doctor with running balances and the doctor’s acknowledgement, which leaves an audit trail.
Connecting the doctor to the drugstore and the CME
Picture a PMR covering a Quezon City district. On Monday they detail Brand X to a pediatrician in a medical arts building. On Thursday they audit the drugstore across the street. Usually that audit is a lone entry that says nothing about Monday’s call.
BeatRoute ties each doctor to their nearby drugstores and chain pharmacy branches during setup. When the rep runs an RCPA (retail chemist prescription audit) at one of them, the brands it dispenses land on the doctor’s record by itself. Now the doctor’s stated intent and the drugstore’s actual dispensing sit side by side. It cannot prove one doctor’s prescribing, because a drugstore fills prescriptions from many doctors. It is still the nearest field signal that detailing is turning into prescriptions.

CMEs, seminars and other doctor meetings follow the same logic. BeatRoute takes each event from budget request to approval to attendance, tagged to every doctor who came. Before a follow-up call, the rep sees that this doctor attended two events. Event planners can check whether drugstores near the attendees dispensed more of the brand afterwards.
The one check to run in any demo: ask to open a single doctor’s page. The calls, the drugstore audits and the CMEs should all be there. If they are not, your reps will keep rebuilding that picture in Excel.
What a district manager sees before the cycle closes
A coverage gap found at the end-of-cycle review is already too late to fix. BeatRoute shows planned versus actual coverage on the same day. When an area falls below its visit norm, the district manager gets an alert while there is still time to act. Managers can also ask BeatRoute Copilot plain questions, such as which Class A doctors nobody has seen in two weeks. That matters when the manager sits in Metro Manila and half the territory is in Mindanao.
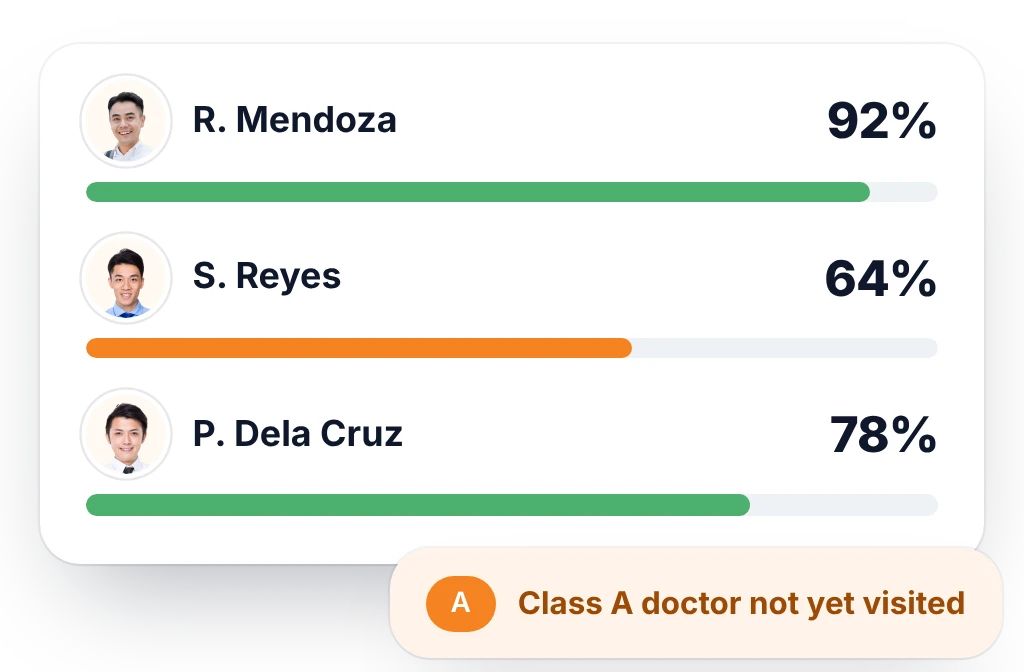
Joint visits are logged in the app, and the manager rates the call, so coaching rests on calls they watched themselves. A submitted report is locked and every edit is recorded, so internal audit can trace each change.
For the wider shift from counting calls to goal-led field work, read from sales force effectiveness to AI-driven SFA.
Rx, OTC or both: matching the setup to your portfolio
The same SFA is set up differently for each kind of team.
| If your team sells | Your field week | Ask to see in the demo |
|---|---|---|
| Specialty Rx brands | A short list of high-value specialists, long calls in hospital clinics, frequent CMEs | Specialty call forms, doctor profiles, event management |
| Branded generics and primary care | Long MD lists across many towns, strict call frequency | Call planning, visit norms, quick call entry, doctor-to-drugstore links |
| OTC and consumer health | Drugstore and chain pharmacy coverage, orders, trade promos, shelf display | Order booking and stockist secondary sales; see SFA for consumer goods |
| Rx and OTC together | Two teams calling on the same towns | Separate app flows and scorecards on one platform |
Try it on two of your territories before you decide
Bring your own data and run these six checks:
- Run an RCPA at a drugstore and show which doctor calls it joins.
- Edit the call form for one specialty while you watch, with no developer.
- Give samples to doctors, then reconcile the PMR’s balance at month end.
- Log a rep’s whole day with mobile data off, as in a provincial town with weak signal, then sync.
- Open the district manager’s view of coverage against plan in the middle of a cycle.
- Show the link to your ERP and to your distributor management system.
Then pilot one territory that performs and one that struggles. First record today’s numbers: Class A doctor coverage, call frequency met, sample balances that reconcile and the hours managers spend building reports. Run a full call cycle so managers act on mid-cycle alerts before you compare.
Nurturemed Pharma, a Philippine pharma company, had low rep productivity, weak sample tracking and problems that surfaced too late. On the BeatRoute platform, it raised the productivity of its PMRs by 20%. Read the Nurturemed case study.
BeatRoute suits pharmaceutical companies and consumer health brands with large teams of medical reps who want detailing and call reporting in the same app. Book a demo to see call forms and doctor profiles built for your own specialties and brands.
Frequently Asked Questions
Is a medical representative app the same as pharma SFA?
A medical representative app is the part of pharma SFA that a PMR carries on the phone: the call plan, call reports, e-detailing and samples. Pharma SFA adds the manager side: approvals, coverage views and reports on the same data. When you compare tools, ask to see both halves.
How is pharma SFA different from MR reporting software?
MR reporting software handles the daily call report (DCR) and the district manager’s review of it. Pharma SFA is the bigger system that report lives in. If daily reports are all you need for now, start there; see our guide to MR reporting software.
What is the difference between SFA and DMS?
SFA runs the work of your field team. A DMS (distributor management system) runs your distributors and stockists: their stock, orders, invoices and claims. Pharma companies selling OTC or branded generics usually need both, connected so an order a rep books at a drugstore reaches the distributor without being keyed in again. See BeatRoute’s distributor management system.
Can PMRs detail doctors remotely?
Yes, for doctors who are hard to catch in person. The rep shares the same approved content on a video call, and the session is saved on the doctor’s record. Our e-detailing software page explains how remote detailing works.
How long does a pharma SFA rollout take?
Most BeatRoute teams go live in 21 days. Larger pharma rollouts take longer, for example when prescription and OTC teams each need their own setup.
